United Ostomy Associations of America
  • HOME
  • OSTOMY INFORMATION
    • Ostomy Information
      • What Is An Ostomy?
      • Living with an Ostomy: FAQs
      • Diet + Nutrition
      • Ostomy Skin Care
      • Sexuality
      • Bill Of Rights
      • New Ostomy Patient Guide
    • My Ostomy
      • Ileostomy
      • Colostomy
      • Urostomy
      • J-Pouch
      • Continent Diversions + Other Ostomy Types
      • Temporary Ostomy
      • Short Bowel Syndrome
      • Español
    • Children to Young Adults with Ostomies
      • Infant/Toddler (0-3 Years)
      • Preschool (3-5 Years)
      • Elementary School (6-9 Years)
      • Pre-Adolescent (10-13 Years)
      • Adolescent (14-18 Years)
      • Young Adult (18-25 Years)
      • Parents & Clinicians Resources
      • Know Your Rights
      • What To Expect After Surgery
      • Odor Control
      • Fast Facts
      • Ostomy Game
    • Crohn’s Disease & Ulcerative Colitis Information
      • Defining, Caring and Treating
      • Preparing for Ostomy Surgery
      • Common Issues, Managing Diet, Mental Health
      • Intimacy, Fertility and Pregnancy
      • Resources
    • General Information
      • UOAA Ostomy Marketplace
      • Product + Supply Information
      • UOAA Resources Library
      • Resources for Nurses/Home Health
      • Travel Tips + TSA
      • Donate Your Ostomy Supplies
      • Emergency Supplies
      • Related Links
      • UOAA Virtual Ostomy Clinic
      • Outpatient Ostomy Services Locator
  • SUPPORT
      • discussion
        Ostomy 101:
        Easily communicate “What is an ostomy?" with our infographic.

        Read More

    • Find Support
      • Support Group Finder
      • Support Group Websites
      • UOAA Virtual Ostomy Clinic
      • Online Peer and Ostomy Support Programs
      • Outpatient Ostomy Services Locator
      • Find a Mental Health Provider
      • Find an Ostomy Nurse
      • Online Discussion Board
      • Apps for Ostomates
      • Emotional Concerns
    • Connect With Us
      • Start/Affiliate Your Group With UOAA
      • Resources For ASGs
      • National Membership
      • Sign Up for Our E-Newsletter
    • Participate
      • Attend An Event
      • Become An Advocate
      • Join Us for a Conference
      • Make A Donation
      • Become a Member of The Phoenix Society
      • Donate Your Ostomy Supplies
      • Take A Survey
  • ADVOCACY
      • portal
        Roadmap to Establishing Outpatient Ostomy Services
        Documents that are available as PDFs to download and print.

        Read More

    • About
      • Advocacy Program
      • Advocacy Priorities
      • 10 Questions to Help You Speak Up and Self-Advocate
    • UOAA Action Center
      • Take Action
      • Competitive Bidding
      • Ostomy and Continent Diversion Patient Bill of Rights Campaign
      • Non-Medical Switching Campaign
      • Join Advocacy Network
      • Find Your Legislator
      • Advocate Tools
    • Other Ways to Get Involved
      • Ostomy Awareness Day
        • Tools
        • Who’s Raising Awareness?
      • Roadmap to Establishing Outpatient Ostomy Services
      • Share Your #MyAccessMatters Story
    • Tools and Resources Library
      • Restroom Access Self-Advocacy Tools
      • Travel Tips + TSA Communication Card
      • Swimming with an Ostomy
      • Workplace Resources
      • Aging with an Ostomy or CD
      • Home Health Tools
      • Webinars
        • Ostomy Supplies and Insurance
        • How to Navigate Insurance and Get Supplies Affordably
    • Take Control of your Healthcare
      • UOAA Virtual Ostomy Clinic
      • Expect More Series & Checklists
      • Additional Advocacy Resources
        • The Americans with Disabilities Act (ADA)
        • Long-Term Care Ombudsman
        • Quality of Care Complaints
        • Medicare Rights Center
  • WHO WE ARE
      • Have a Question for Us?
        UOAA is a 501(c)(3) nonprofit organization that supports, empowers, and advocates for people who have had or who will have ostomy or continent diversion surgery.

        Contact Us

    • About Us
      • Our Mission + History
      • Our Leaders
      • National Sponsors + Partners
      • National Membership
      • Contact Us
    • How We Help
      • Advocacy
      • Awareness
      • Support
      • National Conference
      • Ostomy Nurse Scholarship
    • Get Involved
      • Volunteer
      • Become A Leader
      • Join A Committee
      • Career Opportunities
      • Sign Up for Our E-Newsletter
  • LATEST
  • EVENTS
    • Ostomy Awareness Day
    • Run For Resilience 5K
    • Ostomy Academy
    • Educational Webinars
    • 2027 National Conference
    • Calendar
  • GIVE NOW
  • SEARCH
  • Menu Menu

Tag Archive for: Temporary ostomy

My Appendix Cancer and Ostomy Story

Ileostomy, ostomy reversals, Patient Stories, Personal

Chances of survival from a rare cancer did not look good but that changed thanks to a complex surgery and ostomy, recovery came next.

By Donna Sklener

“Mother of All Surgeries” is the nickname given to the treatment for certain types appendix cancer. Never heard of it? I hadn’t either until it became the biggest challenge of my life. I was diagnosed with Low-Grade Appendiceal Mucinous Neoplasm (LAMN), a cancerous tumor in my appendix. As a further complication, it had escaped my appendix. When this happens, the mucinous cells that usually line the inside of the appendix begin relentlessly reproducing, attaching to the surfaces and organs in the abdomen and filling any open spaces in the abdominal cavity. This version of the disease is called Pseudomyxoma Peritonei, or PMP. The mass of mucinous tumors squeezes the organs, causes intestinal blockages and organ problems, and swells the abdomen. The low-grade version acts slowly and often goes undetected for years, or is found only incidentally when patients are being treated for other abdominal issues. Misdiagnosis is common, and most doctors, even oncologists, have never dealt with appendiceal cancer of any kind.

I first went to my primary care physician complaining of bloating and unexplained weight gain. Looking back, I think this disease was probably active for at least five years before I was bothered enough to approach my provider. My symptoms were relatively minor and I explained them away in my head as being due to reaching my 50’s, being diagnosed with an underactive thyroid, entering perimenopause, and having a desk job. But after I retired at 55 and began walking five miles a day with my husband and still gaining weight (I weighed and looked like I did when eight months pregnant), I decided to look deeper.
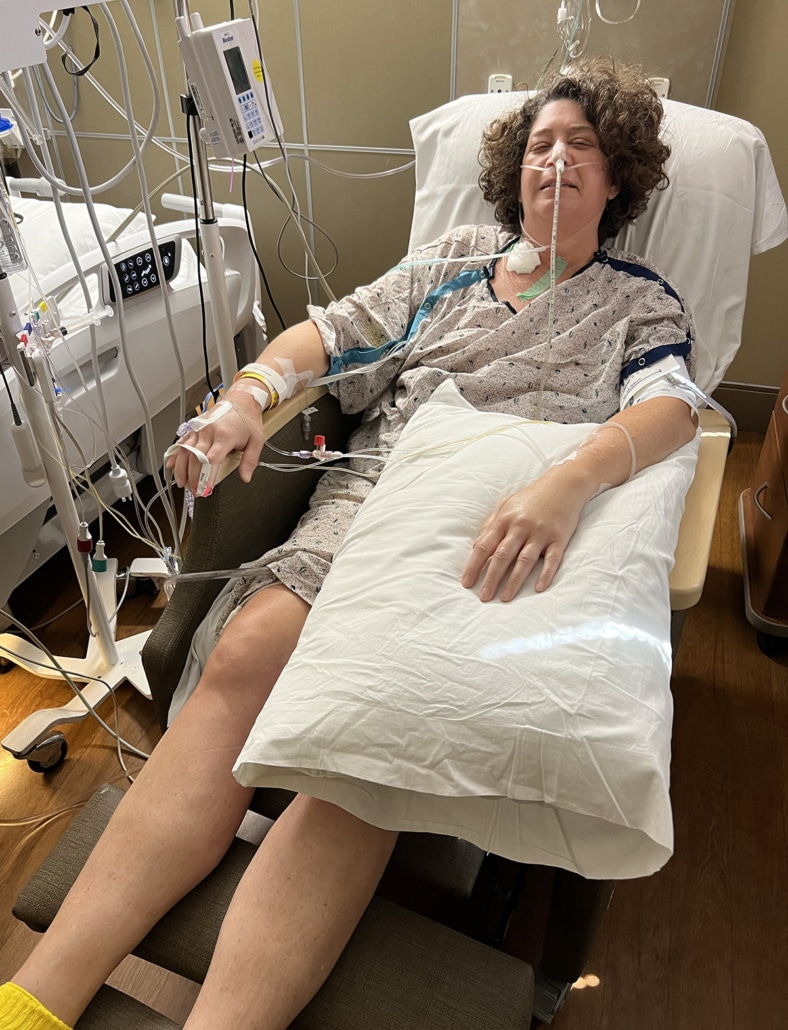
After bloodwork, an endoscopy, colonoscopy, CAT scan, and an aborted appendectomy, I was given a very scary diagnosis of a rare cancer I had never heard of. My first surgeon estimated I had the maximum abdominal tumor load according to the rating system used. He didn’t give me much hope of living past one year, and said three years was not likely. Fortunately, I did research and found that for my type of appendix cancer, it is critical to have an expert surgeon experienced in the massive surgery needed to treat the disease. I needed to travel to a hospital almost four hours from my home, but I am here to share my story three years later because of the expertise, surgical skill, and dedication of my surgeon, Dr. Patrick Wagner of Allegheny Health Network in Pittsburgh, Pennsylvania.

In May of 2023 I underwent a 12-hour surgery – officially referred to as Cytoreductive Surgery with Hyperthermic Intraperitoneal Chemotherapy, or CRS/HIPEC. The surgeon removed my appendix and the right side of my colon. And because the disease had escaped into my abdomen, he also had to scrape or burn off the mucinous cells from my organs. Any that were too affected and I could live without were removed, including my gall bladder, spleen, all reproductive organs, part of my bladder, part of my rectum, peritoneum, and omentum. For most people these would be separate surgeries and few would need all of them. I had them all at once! You can see how the nickname for this extensive and complex surgery came to be. After the cytoreductive part of the surgery, heated chemotherapy chemicals were poured into my open abdomen and circulated for 90 minutes. This HIPEC part of the surgery is done in hopes of killing any remaining mucinous cells that the surgeon could not see to remove.

I woke up with all kinds of new “attachments.” Two nerve blocks in my back, a nasogastric tube going up my nose and down my throat, an ART line in my neck, several IVs, two abdominal drains, a Foley catheter, and an ostomy pouch – because I now had an ileostomy. I was told my ileostomy was temporary, to allow the surgical sites in my colon and rectum to heal.

I was in the hospital for 11 days and lost 30 pounds, most of that during the surgery. The internal healing after CRS/HIPEC takes months. I had lost significant portions of my digestive system, and those remaining had been manipulated, stretched, cleaned, and put back in to a relatively empty abdomen. Everything had to recover, settle, and learn to do its job again, and that took time. I could eat only ice chips while in the ICU, then clear liquids, then soft food on the last couple days in the hospital. Due to the ileostomy, I was told to stick with a low residue, low fiber diet. One day, I’m sure by accident, I was given a ham and cheese sandwich for lunch. I knew enough not to eat that, but thought the mac & cheese that accompanied it was delicious. Until a few minutes later when it came back up. Turns out dairy was something my system was not yet ready for. Recovery involved a lot of trial and error, trying foods and seeing how my body responded. The debilitating cramps and pain (in addition to the expected pain of having an incision from my sternum to my pubic bone with 20+ staples) were scary. I often thought the cramps meant I would split open my anastomoses and have to be opened up again for repair. I also worried because I seemed to have high output into my ostomy bag. I had a large bag after surgery, and the nursing team at the hospital were great about taking care of that. Along with my catheter and drains, they had a lot to empty, measure, and dispose of. Those nurses are truly angels to recovering patients!

After three years of good health and still being “No Evidence of Disease,” I am able to see that my ileostomy was a remarkable aid to my healing and recovery.

A WOC nurse visited twice during my stay to teach me and my husband how to take care of the bag and make changes. It all seemed confusing and complicated, and I didn’t have the attention span (thanks to the pain and related pain management medications) to pay good attention. My husband was a saint and my rock. He took notes, practiced measuring and cutting the wafer, and never showed if he was grossed out. I was grossed out enough for both of us, and it was my body!

Discharge day came and I got set up with a home nursing visit a few days later to help change out the pouch. That nurse had to cut the wafer twice to get it to fit, applied the barrier ring to the wrong side of the wafer and had to start over, and then just a few hours after she left, I had a leak and we had to replace the bag again. My skin was already very sensitive, and the leak and additional change made it even worse. Over the next two months my husband got very good at doing bag changes. I don’t think I could have done them myself. I struggled with emptying the bag for a while because I still had to measure my output for my medical team (high volume worries), so I had to develop a routine of sitting on the edge of our tub to get the right angle to empty into the measuring pitcher, then dispose into the toilet, then clean up and put myself back together. One thing I learned to appreciate was the valve on my high-volume bags. That was much easier and cleaner to deal with than the bags with the open bottom that are rolled up or folded. I tried a few samples of those and just kept thinking, “Why can’t all bags for liquid output have a valve on them?”

I encourage anyone reading this to shed the fear and embarrassment you might be feeling, reach out for support, take advantage of resources that are available to help you

The biggest problem I had was that my stoma was placed right in the crease where I naturally bend at my waist. This led to so many barrier leaks and blow outs. Which then made me very reluctant to leave my house or have visitors. But my family and friends were so understanding and pretended not to hear all the gurgling and gas noises, or the smell that they assured me only I could detect. I am so grateful for their understanding and support.

Walking is really important to recovery from this surgery, so my husband and I started with very short distances – from the bed to the door of my hospital room at first – and worked up to three miles a day before my reversal surgery. I preferred using the high-volume bag, which could get heavy and pull when walking, so I was careful to empty it before we headed out. I tried a few belt options, but nothing ever worked well enough that I could say, “Oh, I forgot I had a bag” when walking around. Walks were uncomfortable and exhausting, but necessary.

Finally, after two months, reversal surgery was scheduled. We again traveled to the out-of-town hospital and as luck would have it, I had a pouch leak while sleeping the night before at a hotel. As we sleepily cleaned up and did a bag change, we laughed (ok, I cried a little too) and were thankful this would be the last one. I showed up at 5:30 am at the hospital with a shiny new pouch to take into surgery. After reversal, it was a much shorter stay at the hospital (four days – enough time to make sure my intestines woke up and were all ok) and the only attachment I had this time was another drain. This one came home with me, but was much easier to deal with than a bag and got removed two weeks later. After the reversal, I had to adjust my diet once again and could transition to more solid food and more fiber, while still experimenting to see what my recovering system could handle. It took several months to get back to eating as I was able to before my diagnosis.

Looking back, I did not approach having an ostomy with the right attitude. I resented that I had one, and felt pretty sorry for myself. I already felt very dependent on my husband as my caregiver during a very difficult surgical recovery, and the ostomy part of that made me feel even worse and magnified my concern that I was a burden to him (a feeling he vehemently denied, and which I am truly able to believe, now that it is in the rear-view window). I did very little research on ostomies, did not seek out helpful resources, and because it was temporary, resigned myself (and my husband) to just suffering through the experience until my reversal. This is not a good way to deal with an ostomy.

After three years of good health and still being “No Evidence of Disease,” I am able to see that my ileostomy was a remarkable aid to my healing and recovery. It gave my system time to heal and helped me get back to the things I enjoy doing, like walking every day, spending time with friends and family, gardening, and traveling the world.

With my disease, if only one mucinous cell remains, there is always a chance that I will have a recurrence and need another surgery – and perhaps another ileostomy or colostomy. I have since learned of many resources such as those from UOAA for ostomates. Next time I will insist on better home nursing support. I will call the help lines at the various supplier companies to explore pouch and attachment options to help with the leaks caused by my specific anatomy. I’ll use the wonderful resources at ostomy.org now that I know they exist. I can’t imagine how much better my whole experience would have been with a fellow ostomate to talk to and the support of this fantastic organization!

So, I encourage anyone reading this to shed the fear and embarrassment you might be feeling, reach out for support, take advantage of resources that are available to help you, and realize that although few people love their ostomy, we can appreciate what it does for us, and find the best way of living a full life with it. I wish everyone the very best experience possible.



August 7, 2026
https://www.ostomy.org/wp-content/uploads/2026/08/Donna_Venice.jpg 1334 1800 Contributor https://www.ostomy.org/wp-content/uploads/2017/02/UOAAlogofinal2.png Contributor2026-08-07 10:24:572026-08-07 12:43:45My Appendix Cancer and Ostomy Story

Twists and Turns of J-Pouch Recovery

Continent Diversions, IBD, Ileostomy, J-Pouch, ostomy reversals

By Robin Glover

The recovery process for a j-pouch is just that. It’s a process. It takes time and patience and is different for everyone. For some, it can be relatively easy. For others, it can be a winding path with twists and turns just like the colon that was removed for it.

But one thing is the same for practically everyone: j-pouch surgery offers hope for a return to a life that’s less encumbered by the alternatives. Seriously, who doesn’t want to poop out of their butt again if given the opportunity? Oh, and getting rid of that disease-ravaged large intestine is a plus, too.

What Is A J-Pouch?

In case you’re reading this to research information for yourself, friend or family member, here’s a quick explanation of what a j-pouch is:

Medically known as Ileal Pouch Anal Anastomosis (IPAA) surgery, it involves removing the entire colon and rectum and then connecting the small intestine directly to the anus. The term j-pouch refers to the shape of the “pouch” that’s created when the surgeon folds the small intestine on itself and creates a reservoir to hold waste until it is passed through the anus. It can also be known as an s-pouch or w-pouch based on how it’s surgically constructed. J-Pouch surgery is most often done in cases of ulcerative colitis where there is no disease in the small intestine or as a result of FAP, colorectal cancer or a bowel perforation.

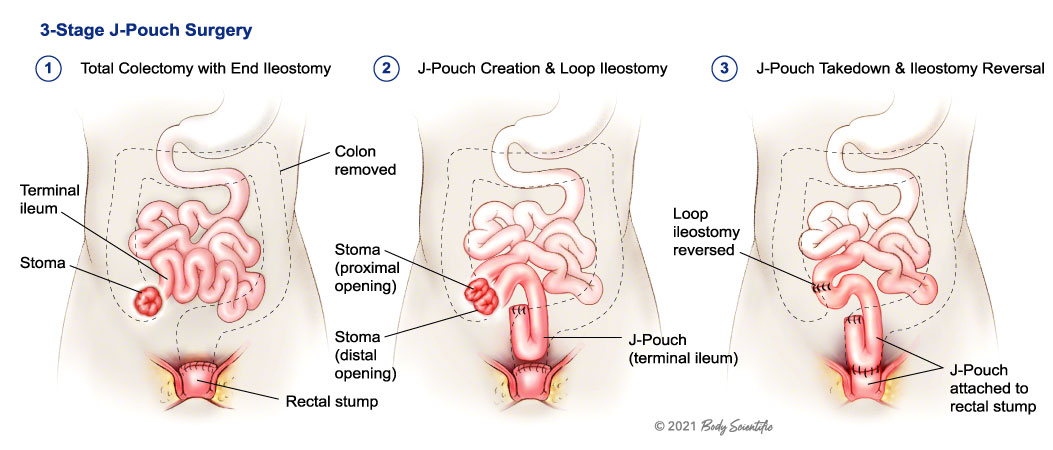
The surgery for a j-pouch almost always involves two or three steps. The first step, and usually the more major surgery, is to remove the large intestine. At the same time, an ileostomy is created that will be used until the small intestine is reattached. This will be a temporary external pouch.

Stages of J-Pouch Surgery

Depending on individual circumstances, the first surgery can also involve removing the rectum and creating the internal j-pouch. However, it can also be its own separate procedure. But either way, the final step is to reverse the ileostomy and connect the small intestine to the anus. At this point, no external pouch is needed and the traditional route of passing stool can resume.

Be aware that the patient has the right to decide between a J-pouch or keeping the ostomy and should know not all temporary ostomies are able to be taken down and not all J-pouches are able to be connected.

Early Recovery From J-Pouch Surgery

It’s an exciting experience when you wake up from the final surgery and see that there’s no longer a need to have a pouch attached to you. What was once your stoma is now a still pretty nasty wound, but one that will heal and become just another proud scar.

Things won’t be working quite yet though. It will be a few days before you actually have a bowel movement. Sometimes it can take longer, but that’s not a big deal. When you’re in the hospital you’ll be monitored and well taken care of. You likely won’t go home until your doctors are sure everything is working correctly, including being able to eat and pass solid food.

Everything that comes out will still be liquid, though. It will be a little bit before you start passing anything even semi-solid. And you might not ever get to that point or only have it happen on rare occasions. There’s nothing unusual about that.

J-Pouch Guide

Diet Right After Going Home

The diet you follow after getting home from the hospital will be communicated to you by your doctor and you’ll probably go home with many guides and resources. Mainly, staying hydrated is very important and avoid raw fruits or vegetables, nuts, whole grain, seeds, or anything else that doesn’t digest in around two hours. Since you no longer have a large intestine, food has much less time to be processed and if you eat a handful of nuts they’re going to come out the same way they went down.

Check the Eating with an Ostomy Guide for a much more complete diet guideline.

But, even worse, it can cause a blockage. Blockages are the bane of a j-pouch’s existence. You need to be careful about what you eat (typically called a “low residue” diet) and chew your food thoroughly. Chew extra. And then some more. Take small bites and don’t take any risks right away. Introduce new foods slowly.

NOTE: Your doctor or dietician will know the best foods to eat and what to avoid for your specific needs. Always follow their directions before anything you read on the internet.

Getting To Know Your J-Pouch

It can take a while after surgery to completely adjust to your new plumbing. You’ll learn what foods are “safe foods” and which to avoid. You’ll also learn about how your j-pouch behaves and how it affects your daily life.

For example, you’ll start to get an idea of how many times per day you’ll go to the bathroom and what consistency you can expect. You’ll also learn what each sense of urgency means and when you need to go to the bathroom right away and when you can hold it. It will feel like you need to go to the bathroom a lot and you’ll probably actually need to at the beginning. But, over time, your j-pouch will stretch and grow to be able to hold more before needing to be emptied.

Ideally, after everything settles down, you will only go to the bathroom 4 to 8 times a day and it will be a simple and quick emptying process.

You’ll Experience Butt Burn

Speaking of going to the bathroom a lot, you may experience what is known as “butt burn.” This is because, on top of going to the bathroom more often, without a large intestine your stool will be much more acidic from digestive enzymes.

It’s necessary to take special care and make sure everything is extra clean. A bidet is a great idea because rubbing with toilet paper can also cause irritation. There are also many creams and lotions you can use to soothe and protect. Zinc-based lotions are a good place to start. And get some disposable gloves while you’re at it.

You may go to the bathroom up to 20 times a day (or more) and experience irritation from going so much. But, it will get better as you learn more about your j-pouch and develop processes that work best for you. In the end (no pun intended), you’ll get to a point where you’re comfortable and know how to manage it like an expert.

Ideally, after everything settles down, you will only go to the bathroom 4 to 8 times a day and it will be a simple and quick emptying process.

It’s Not Always Easy

As mentioned, j-pouch recovery is a process. At the beginning, there will be accidents (typically nighttime) and discomfort. It’s a whole new way of digesting food and your body needs time to adjust. And you will need time to adjust to it too. It’s a major change.

Be aware of possible complications such as pouchitis and tell your doctor if you have more frequent or blood in your bowel movements.If you have a j-pouch or need one, you’ve already been through a lot. You know you’re resilient and can make it through almost anything. This is just another step in your journey.

Don’t let any of this discourage you. There’s a reason you decided to get a j-pouch and there’s a wealth of resources and support out there to help. Everything you will experience has been experienced before and the j-pouch community is always ready to help. But keep in mind that social media is often a place to vent so you might see more negative than positive posts.

So focus on the good, be patient, and look forward to enjoying pooping out of your butt again!


Robin Glover is a writer based in the Houston area. He has a permanent ostomy after being diagnosed with Crohn’s Disease in 2017.

February 28, 2022
https://www.ostomy.org/wp-content/uploads/2022/02/J-Pouch-Recovery-twists-and-turns.jpeg 924 1640 Contributor https://www.ostomy.org/wp-content/uploads/2017/02/UOAAlogofinal2.png Contributor2022-02-28 12:36:302022-03-01 14:33:39Twists and Turns of J-Pouch Recovery

Living With An Ostomy: An 18-Year-Old’s Perspective

IBD, Ileostomy, Patient Stories, Personal

By Steven Berit

I fainted the first time I lost a tooth. Not from the actual pain of the removal, but from the sight of the blood dripping from my mouth. I also fainted during a health talk in the sixth grade. Most people would call me “squeamish,” and I would agree. The sight of blood or even the mention of anything related to the human body can easily send me into a spiral of emotions typically resulting in me waking up in the nurse’s office. So, you can imagine my apprehension when the doctors first suggested the idea of me receiving a colectomy.

Hi, I’m Steven Berit. I’m eighteen years old and I am a senior in high school. I live in Pennsylvania with my mom, my dad, and my sister when she is home from college. I live a pretty “normal” life. I go to school, play football, and hang out with friends just like anyone else my age would do. The only difference between me and everyone else is that I have an ostomy bag and they don’t. This small detail isn’t even noticeable for most, but at first, it certainly was noticeable to me.

I was sixteen when I was first diagnosed with ulcerative colitis. The next year and a half would be full of trial and error, and with each passing day the errors stuck out more and more. Mesalamine, Remicade, Entyvio, and Xeljanz were just a few of the never-ending drugs that I was prescribed. The only thing that seemed to be working was steroids, but both my doctors and my acne-ridden face agreed that this was not a permanent solution. Finally, in July of 2019 while in my latest stint on the 5th floor of the Children’s Hospital of Philadelphia, I made the decision to say good-bye to my very inflamed, friend- my colon.

I don’t remember much of the first night following the surgery, but the next couple of days stick out in my mind vividly. Well, I mean I clearly remember the restless nights. As for the actual stoma itself, this took me some time before I had my first encounter with it eye-to-eye or eye-to-intestine in this case. The second night was one of the worst nights of my life. I guess the anesthesia had worn off and with it came the regret. Yes, that second night I thought I made the biggest mistake of my life. There I laid in a hospital bed way too small for my eighteen-year-old frame contemplating if I could ever recover from this setback in my life.

Well, the sun rose and with it time for my first bag change. I remember screaming- a lot. They told me that the stoma couldn’t feel pain, but what they failed to mention was that I could still feel the pain of my hair ripping off my body as they pulled the adhesive off my skin. Trust me your average eighteen-year-old boy has plenty of hair to go around, but your eighteen-year-old boy that has been steroids for the last year and change has more hair than one would openly like to admit. But, as the bag came off, I got my first glimpse of my future in the form of a beautiful, red stump known as my stoma.

The next couple of weeks would come and go with relatively little struggle, but as summer came to an end my biggest challenge approached- going to school. I tried every possible combination of tucking my bag into my pants until I came to the realization that no one cared. Either people didn’t take notice of the bag of stool attached to my body or they too were busy and caught up with their own lives to care about what secret I kept hidden behind my shirt. It was my first time since being diagnosed with UC where I felt “normal” at school. Which was odd because to most this was the least “normal” I had ever been.

No, my journey with my ostomy was not one I would describe as love at first sight. But it has grown on me over time. Yes, I still need my parents help to change my bag every three days, but the once shrieks of pain have now subsided into murmurs. I now go to school every day like a new person. I no longer have fears of finding where the nearest bathroom is or if I am going to be able to take a test for thirty minutes without a wave of urgency coming over me forcing me to drop everything and make a mad dash to the nearest restroom. Instead, most days go by without any thoughts of UC or stomas crossing my mind.

As I come closer every day to my reversal surgery in December, I begin to wonder if I would be able to live with this bag for the rest of my life, and after some thought, I honestly believe I would be able to. UC has taught me over the years that I can overcome anything and the ostomy bag was just the latest thing I had to overcome. If I can go from fainting over a loose tooth to conquering a disease that once bullied me then I can overcome any challenges that may come my way. The once terrifying ostomy bag has become a cherished friend of mine who I will never forget even when it is gone. I cried when I had my first tooth removed. I may also cry when I have my ostomy removed, but I think these tears will fall for a completely different reason.

November 14, 2019
https://www.ostomy.org/wp-content/uploads/2019/11/Steven_Lede-photo.jpg 2487 4957 Contributor https://www.ostomy.org/wp-content/uploads/2017/02/UOAAlogofinal2.png Contributor2019-11-14 10:21:002020-05-19 10:57:15Living With An Ostomy: An 18-Year-Old’s Perspective

Facts About Ostomy Reversals

Colorectal Cancer, Colostomy, Ileostomy, ostomy reversals

Colorectal Cancer: Be informed if you are a candidate for an ostomy reversal 


By Joanna Burgess-Stocks, BSN, RN, CWOCN


  • Not everyone who has an ostomy as a result of colorectal cancer and other diseases will have the option of having their ostomy reversed.  Some people will need to keep their ostomy for life.


  • Your surgeon will determine when an ostomy will be reversed. There are many factors that determine a reversal such as the extent of the disease, a patient’s overall health and treatment process (radiation and chemotherapy).  Most patients with temporary ostomies will have the ostomy for about 3-6 months.


  • Surgery for reversal of an ostomy is usually much less involved than the surgery that you had to create the ostomy. So if you are feeling nervous, keep that in mind. A typical hospital course is 3-4 days on average.


  • For some patients, interrupting bowel function with a temporary ileostomy increases the chances that you will experience alterations in bowel function after reversal of your stoma. These symptoms can include rectal urgency, frequency, fragmentation of stool and incontinence. It is important that you notify your surgeon as soon as possible with these symptoms. Treatment includes behavioral strategies based on the symptoms and includes dietary modifications, incontinence products, skin care (use of barrier creams such as zinc oxide) and medications such as loperamide. More involved but helpful recommendations are pelvic muscle retraining (PMR) to regain sphincter strength and biofeedback. This therapy is done by a highly trained physical therapist.


  • Some physical therapists recommend PMR prior to surgery or radiation to assess muscles and teach strategies for ongoing muscle strengthening that can be carried over after surgery. This helps to address any coordination or existing weakness prior to radiation due to chemo or post-operative recovery. If PMR is recommended after surgery, it is best to wait at least 6 weeks and with the surgeon’s approval.
February 13, 2018
https://www.ostomy.org/wp-content/uploads/2018/02/Ostomy-Reversal-Facts.png 788 940 Contributor https://www.ostomy.org/wp-content/uploads/2017/02/UOAAlogofinal2.png Contributor2018-02-13 12:23:232020-06-21 09:16:05Facts About Ostomy Reversals

Our Categories

Advocacy (82) Body Image (3) Caregivers (21) Colorectal Cancer (19) Colostomy (142) Continent Diversions (8) Digital Sponsor (80) Disaster Preparation (4) Emotional Health (64) Events (33) Exercise/Sports (49) Fashion/Clothing (11) Healthcare (23) IBD (57) Ileostomy (191) J-Pouch (8) jejunostomy (8) Membership (3) Nutrition (19) Ostomy 5k (21) Ostomy 5k (17) Ostomy Awareness (56) Ostomy Basics (56) Ostomy News (99) Ostomy Nurse (15) ostomy reversals (13) Ostomy Supplies (3) Ostomy Tips (96) Ostomy Videos (4) Patient Stories (104) Pediatric Ostomy (5) Personal (69) Sexuality (12) Short Bowel Syndrome (17) Skin Care (10) Social Life (5) Support Group News (13) Support Resources (16) Teens (4) Travel (12) UOAA Conference (18) UOAA History (3) UOAA Volunteers (5) Urostomy (114) Young Adult (10)

Support Us:

Your Donation Funds UOAA Educational Programs:

DONATE TODAY
SUSTAINING GIFT
BECOME A MEMBER
UOAA E-NEWS SIGN UP
Get updates on events, national advocacy and important topics in the ostomy and continent diversion community.

Contact Us


United Ostomy Associations of America
P.O. Box 2293
Biddeford, ME 04005-2293

Virtual Ostomy Clinic

Contact UOAA

Donate Your Supplies

Call us toll-free at: 1-800-826-0826.
Our Information Line hours are Monday-Friday, 9am to 3pm EST. If you have an emergency, please dial 911 or contact your local medical professional.

Please understand that UOAA is a private, nonprofit, advocacy and informational organization. We are not a medical facility and we do not have medical or legal professionals on staff. Therefore, UOAA does not provide Medical, Mental Health, Insurance or Legal Advice. Visit UOAA Virtual Ostomy Clinic provided by The Wound Company for non-emergency, virtual ostomy support.

Privacy Policy

Get Involved

UOAA is the leading organization proactively advocating on behalf of the ostomy community. Recognizing that we are always stronger together, we encourage everyone to get involved by joining our Advocacy Network. We’ve also created several Advocacy Tools and Resources to help you successfully advocate on behalf of the ostomy community to ensure every ostomate receives quality care.

UOAA Run for Resilience Logo

UOAA does not and shall not discriminate on the basis of race, color, religion (creed), gender, gender expression, age, national origin (ancestry), disability, marital status, sexual orientation, or military status, in any of its activities or operations.

Digital Health Award
© 2005-2026, UOAA. All Rights Reserved l Design by Tap House Media
  • Link to Facebook
  • Link to X
  • Link to Pinterest
  • Link to LinkedIn
  • Link to Youtube
  • Link to Mail
  • Link to Instagram
Scroll to top Scroll to top Scroll to top





